Dst70025 591 598.Pdf
Total Page:16
File Type:pdf, Size:1020Kb
Load more
Recommended publications
-

Differences in Genotype, Clinical Features, and Inflammatory
RESEARCH Differences in Genotype, Clinical Features, and Inflammatory Potential of Borrelia burgdorferi sensu stricto Strains from Europe and the United States Tjasa Cerar,1 Franc Strle,1 Dasa Stupica, Eva Ruzic-Sabljic, Gail McHugh, Allen C. Steere, Klemen Strle Borrelia burgdorferi sensu stricto isolates from patients with B. afzelii, which usually remains localized to the skin, with erythema migrans in Europe and the United States and B. garinii, which is usually associated with nervous were compared by genotype, clinical features of infection, system involvement (1). B. burgdorferi infection is rare in and inflammatory potential. Analysis of outer surface pro- Europe; little is known about its clinical course there. In tein C and multilocus sequence typing showed that strains the United States, B. burgdorferi is the sole agent of Lyme from these 2 regions represent distinct genotypes. Clinical borreliosis; in the northeastern United States, it is particu- features of infection with B. burgdorferi in Slovenia were similar to infection with B. afzelii or B. garinii, the other 2 larly arthritogenic (1,2). For all 3 species, the first sign of Borrelia spp. that cause disease in Europe, whereas B. infection is often an erythema migrans lesion. However, B. burgdorferi strains from the United States were associ- burgdorferi infection in the United States is associated with ated with more severe disease. Moreover, B. burgdorferi a greater number of disease-associated symptoms and more strains from the United States induced peripheral blood frequent hematogenous dissemination than B. afzelii or B. mononuclear cells to secrete higher levels of cytokines garinii infection in Europe (4–7). -

Inflammatory Or Infectious Hair Disease? a Case of Scalp Eschar and Neck Lymph Adenopathy After a Tick Bite
Case Report ISSN: 2574 -1241 DOI: 10.26717/BJSTR.2021.35.005688 Adherent Serous Crust of the Scalp: Inflammatory or Infectious Hair Disease? A Case of Scalp Eschar and Neck Lymph Adenopathy after a Tick Bite Starace M1, Vezzoni R*2, Alessandrini A1 and Piraccini BM1 1Dermatology - IRCCS, Policlinico Sant’Orsola, Department of Specialized, Experimental and Diagnostic Medicine, Alma Mater Studiorum, University of Bologna, Italy 2Dermatology Clinic, Maggiore Hospital, University of Trieste, Italy *Corresponding author: Roberta Vezzoni, Dermatology Clinic, Maggiore Hospital, University of Trieste, Italy ARTICLE INFO ABSTRACT Received: Published: April 17, 2021 The appearance of a crust initially suggests inflammatory scalp diseases, although infectious diseases such as impetigo or insect bites should also be considered among April 27, 2021 the differential diagnoses. We report a case of 40-year-old woman presentedB. Burgdorferi to our, Citation: Starace M, Vezzoni R, Hair Disease Outpatient Service with an adherent serous crust on the scalp and lymphadenopathy of the neck. Serological tests confirmed the aetiology of while rickettsia infection was excluded. Lyme borreliosis can mimic rickettsia infection Alessandrini A, Piraccini BM. Adherent and may present as scalp eschar and neck lymphadenopathy after a tick bite (SENLAT). Serous Crust of the Scalp: Inflammatory Appropriate tests should be included in the diagnostic workup of patients with necrotic or Infectious Hair Disease? A Case of Scalp scalpKeywords: eschar in order to promptly set -

Toward a Better Understanding of the Spectrum of Morphea
STUDY ONLINE FIRST High Frequency of Genital Lichen Sclerosus in a Prospective Series of 76 Patients With Morphea Toward a Better Understanding of the Spectrum of Morphea Virginie Lutz, MD; Camille Francès, MD, PhD; Didier Bessis, MD; Anne Cosnes, MD; Nicolas Kluger, MD; Julien Godet, PhD; Erik Sauleau, PhD; Dan Lipsker, MD, PhD Objective: To compare the frequency of genital lichen diagnosis was 54 (13-87) years. Forty-nine patients had sclerosus (LS) in patients with morphea with that of con- plaque morphea, 9 had generalized morphea, and 18 had trol patients. linear morphea. Three patients (3%) in the control group and 29 patients (38%) with morphea had LS (odds ra- Design: A prospective multicenter study. tio,19.8; 95% CI, 5.7-106.9; PϽ.001). Twenty-two pa- tients with plaque morphea (45%) and only 1 patient with Setting: Four French academic dermatology depart- linear morphea (6%) had associated genital LS. ments: Strasbourg, Montpellier, Tenon Hospital Paris, and Henri Mondor Hospital Cre´teil. Conclusions: Genital LS is significantly more frequent in patients with morphea than in unaffected individu- Patients: Patients were recruited from November 1, 2008, als. Forty-five percent of patients with plaque morphea through June 30, 2010. Seventy-six patients with mor- have associated LS. Complete clinical examination, in- phea and 101 age- and sex-matched controls, who un- cluding careful inspection of genital mucosa, should there- derwent complete clinical examination, were enrolled. fore be mandatory in patients with morphea because geni- tal LS bears a risk of evolution into squamous cell Interventions: A complete clinical examination and, if deemed necessary, a cutaneous biopsy. -

Erythema Marginatum
Figurative Erythemas Michelle Goedken, DO Affiliated Dermatology Scottsdale, AZ Figurative Erythemas • Erythema annulare centrifugum • Erythema marginatum • Erythema migrans • Erythema gyratum repens • Erythema multiforme Erythemas • Erythemas represent a change in the color of the skin that is due to the dilation of blood vessels, especially those in the papillary and reticular dermis • The color is blanchable and most last for days to months • Figurative erythemas have an annular, arciform or polycyclic appearance ERYTHEMA ANNULARE CENTRIFUGUM ERYTHEMA ANNULARE CENTRIFUGUM • Pathogenesis: EAC represents a reaction pattern or hypersensitivity to one of many antigens – IL-2 and TNF-alpha may have a role – Most patients do not have an underlying disease identified ERYTHEMA ANNULARE CENTRIFUGUM • Associated with: – Infection » Dermatophytes and other fungi (Candida and Penicillium in blue cheese) » Viruses: poxvirus, EBV, VZV, HIV » Parasites and ectoparasites – Drugs: diuretics, antimalarials, gold, NSAIDs, finasteride, amitriptyline, etizolam, Ustekinumab (2012) ERYTHEMA ANNULARE CENTRIFUGUM – Foods – Autoimmune endocrinopathies – Neoplasms (lymphomas and leukemias) – Pregnancy – Hypereosinophilic syndrome – Lupus (2014) ERYTHEMA ANNULARE CENTRIFUGUM http://www.dermaamin.com Rongioletti, F., Fausti, V., & Parodi, A ERYTHEMA ANNULARE CENTRIFUGUM • 2 major forms: – Superficial: classic trailing scale, may have associated pruritus – Deep: infiltrated borders, usually no scale, edges are elevated, usually not pruritic ERYTHEMA ANNULARE CENTRIFUGUM -
Belly Button…
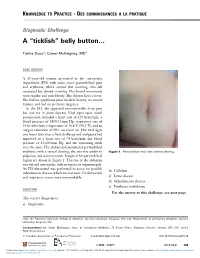
KNOWLEDGE TO PRACTICE DES CONNAISSANCES À LA PRATIQUE Diagnostic Challenge A “ticklish” belly button… Tahira Daya*; Conor McKaigney, MD† CASE HISTORY A 42-year-old woman presented to the emergency department (ED) with acute onset periumbilical pain and erythema, which started that morning. She felt nauseated but denied vomiting. Her bowel movements were regular and non-bloody. She did not have a fever. She had no significant prior medical history, no recent trauma, and had no previous surgeries. In the ED, she appeared uncomfortable from pain but was not in acute distress. Vital signs upon initial presentation included a heart rate of 120 beats/min, a blood pressure of 145/111 mm Hg, respiratory rate of 16 breaths/min, temperature of 36.8°C (98.2°F), and an oxygen saturation of 99% on room air. Her vital signs two hours later after a fluid challenge and analgesics had improved to a heart rate of 74 beats/min and blood pressure of 132/83 mm Hg, and the remaining vitals were the same. Her abdomen demonstrated periumbilical erythema, with a central clearing; the area was tender to Figure 1. Periumbilical rash with central clearing. palpation, and warm to touch. Images of her periumbilical region are shown in Figure 1. The rest of the abdomen was soft and non-tender, with no masses or organomegaly. An ED ultrasound was performed to assess for possible b) Cellulitis subcutaneous abscess, which was not seen. Cardiovascular and respiratory exams were unremarkable. c) Lyme disease d) Subcutaneous abscess e) Erythema multiforme QUESTION For the answer to this challenge, see next page. -

Lyme Disease Diagnostic Support Tool
1 / 11 For further details, click on the DIAGNOSTIC SUPPORT TOOL underlined words. Localized and disseminated stages of Lyme disease This diagnostic support tool is intended mainly for primary care clinicians. It is provided for information purposes only and should not replace the judgement of the clinician who performs the activities reserved under a statute or regulation. The recommendations in this tool were developed using a systematic process and are supported by the scientific literature and the knowledge and experience of Québec health professionals, experts and patients. For further details, go to the “Publications” section of INESSS’s website inesss.qc.ca. This tool does not deal with other tick-borne infections or with the much-debated form of Lyme disease, which is sometimes referred to as the chronic form. WHAT IS LYME DISEASE ? WHAT ARE THE DIFFERENT STAGES OF THE DISEASE? GENERAL INFORMATION • Lyme disease is an infectious disease caused by bacterial Localized stage (sometimes called the early stage): Beginning Patient with a tick genospecies of Borrelia burgdorferi, which are transmitted of the infection before dissemination of the bacteria in the • If tick is attached, refer to the procedure for removing it. to humans by black-legged ticks that are carriers. bloodstream. • Refer to the tick surveillance procedure. • Main manifestation observed: • It is a notifiable disease (MADO) • Consult the decision support tool or the Québec’s national and is on the increase in Québec. Not always present or noticed. medical protocol on post-exposure prophylaxis. • It can affect several anatomical systems at the same time. If present, usually appears • Identifying the tick and obtaining proof that it carries of Lym 3 to 30 days after infection or e d B. -

A Case of Discoid Lupus Erythematosus Masquerading As Acne
Letters to the Editor 175 A Case of Discoid Lupus Erythematosus Masquerading as Acne Anastasios Stavrakoglou, Jenny Hughes and Ian Coutts Department of Dermatology, Hillingdon Hospital, Pield Heath Road, Uxbridge UB8 3NN, UK. E-mail: [email protected] Accepted July 4, 2007. Sir, On examination he had a widespread acneiform eruption, We describe here a case of discoid lupus erythemato- which was distributed on his face, pre-sternal area and back, particularly down the length of his spine. He had multiple sus (DLE) masquerading as acne vulgaris. Cutaneous brown-red follicular papules and open comedones, especially manifestations of lupus erythematosus (LE) are usually on his back, and hypopigmented atrophic scars. There were no characteristic enough to permit straightforward diagnosis. pustules or nodulocystic lesions (Fig. 1). However, occasionally they may be variable and mimic Treatment was started with erythromycin 500 mg bid and other dermatological conditions. adapalene cream once daily to treat a presumed diagnosis of acne vulgaris. He was seen 3 months later with a deterioration Acneiform presentation is one of the most rarely re- of his clinical appearance and increased pruritus. This was ported and one of the most confusing, as it resembles a attributed by the patient to increased sun exposure. The photo- very common inflammatory skin disease and therefore aggravation, the intense pruritus and the absence of pustules can be easily missed clinically. Only 5 cases have been and nodulocystic lesions broadened our differential diagnosis reported in the literature (1–4). The patient described and therefore diagnostic biopsies were obtained. A biopsy from the back where the rash was most suggestive clinically here presented with a widespread pruritic acneiform of acne vulgaris, showed hyperkeratosis with orthokeratosis, rash, which was initially diagnosed and treated as epidermal atrophy and extensive vacuolar degeneration of the acne vulgaris with no response. -

Biomaterials and the Foreign Body Reaction: Surface Chemistry Dependent Macrophage Adhesion, Fusion, Apoptosis, and Cytokine Production
BIOMATERIALS AND THE FOREIGN BODY REACTION: SURFACE CHEMISTRY DEPENDENT MACROPHAGE ADHESION, FUSION, APOPTOSIS, AND CYTOKINE PRODUCTION by JACQUELINE ANN JONES Submitted in partial fulfillment of the requirements For the degree of Doctor of Philosophy Dissertation Advisor: James Morley Anderson, M.D., Ph.D. Department of Biomedical Engineering CASE WESTERN RESERVE UNIVERSITY May, 2007 CASE WESTERN RESERVE UNIVERSITY SCHOOL OF GRADUATE STUDIES We hereby approve the dissertation of ______________________________________________________ candidate for the Ph.D. degree *. (signed)_______________________________________________ (chair of the committee) ________________________________________________ ________________________________________________ ________________________________________________ ________________________________________________ ________________________________________________ (date) _______________________ *We also certify that written approval has been obtained for any proprietary material contained therein. Copyright © 2007 by Jacqueline Ann Jones All rights reserved iii Dedication This work is dedicated to… My ever loving and ever supportive parents: My mother, Iris Quiñones Jones, who gave me the freedom to be and to dream, inspires me with her passion and courage, and taught me the true meaning of friendship. My father, Glen Michael Jones, a natural-born teacher who taught me to be an inquisitive student of life, inspires me with his strength and perseverance, and gave me his kind, earnest heart that loves deeply and always -

LICHEN SCLEROSUS Lichen Sclerosus (Sometimes Called Lichen
LICHEN SCLEROSUS Lichen Sclerosus (sometimes called lichen sclerosus at atrophicus, or LS&A) is a skin condition that is most common on the vulva of older women who have gone through menopause. However, lichen sclerosus sometimes affects girls before puberty, as well as young adult women, and the penis of uncircumcised males. In females, lichen sclerosus can affect rectal skin also. Only rarely does lichen sclerosus affect skin outside the genitalia, and this is usually the back, chest or abdomen. Lichen sclerosus almost never appears on the face or hands. The causes of lichen sclerosus are not completely understood, but a main cause is an over-active immune system. The immune system, that part of the body that fights off infection, becomes over-active and attacks the skin by mistake. Why this happens is not known. Lichen sclerosus typically appears as white skin that is very itchy. The skin is also fragile, so rubbing and scratching can cause breaks, cracks and bruises that hurt. Sexual activity is often painful or impossible. Untreated, lichen sclerosus can cause scarring and, occasionally, narrowing of the opening of the vagina in women. In boys and men, the foreskin can scar to the head of the penis. Untreated lichen sclerosus is also associated with skin cancer of the vulva in about one in thirty women. There is also an increased risk of skin cancer of the penis in men. These risks can be lowered when lichen sclerosus is well-controlled. Irritating creams, unnecessary medication, soaps and over washing should be avoided. Washing should be limited to once daily with clear water only. -

2016 Essentials of Dermatopathology Slide Library Handout Book
2016 Essentials of Dermatopathology Slide Library Handout Book April 8-10, 2016 JW Marriott Houston Downtown Houston, TX USA CASE #01 -- SLIDE #01 Diagnosis: Nodular fasciitis Case Summary: 12 year old male with a rapidly growing temple mass. Present for 4 weeks. Nodular fasciitis is a self-limited pseudosarcomatous proliferation that may cause clinical alarm due to its rapid growth. It is most common in young adults but occurs across a wide age range. This lesion is typically 3-5 cm and composed of bland fibroblasts and myofibroblasts without significant cytologic atypia arranged in a loose storiform pattern with areas of extravasated red blood cells. Mitoses may be numerous, but atypical mitotic figures are absent. Nodular fasciitis is a benign process, and recurrence is very rare (1%). Recent work has shown that the MYH9-USP6 gene fusion is present in approximately 90% of cases, and molecular techniques to show USP6 gene rearrangement may be a helpful ancillary tool in difficult cases or on small biopsy samples. Weiss SW, Goldblum JR. Enzinger and Weiss’s Soft Tissue Tumors, 5th edition. Mosby Elsevier. 2008. Erickson-Johnson MR, Chou MM, Evers BR, Roth CW, Seys AR, Jin L, Ye Y, Lau AW, Wang X, Oliveira AM. Nodular fasciitis: a novel model of transient neoplasia induced by MYH9-USP6 gene fusion. Lab Invest. 2011 Oct;91(10):1427-33. Amary MF, Ye H, Berisha F, Tirabosco R, Presneau N, Flanagan AM. Detection of USP6 gene rearrangement in nodular fasciitis: an important diagnostic tool. Virchows Arch. 2013 Jul;463(1):97-8. CONTRIBUTED BY KAREN FRITCHIE, MD 1 CASE #02 -- SLIDE #02 Diagnosis: Cellular fibrous histiocytoma Case Summary: 12 year old female with wrist mass. -

Dermatose Degenerativa Induzida Por D-Penicilamina Em Paciente Com Doença De Wilson
Revista SPDV 76(2) 2018; D-Penicillamine induced degenerative dermopathy; Rui Pedro Santos, Joana Gomes, Celeste Brito. Caso Clínico Dermatose Degenerativa Induzida por D-penicilamina em Paciente com Doença de Wilson Rui Pedro Santos1, Joana Gomes2, Celeste Brito2 1Interno de Dermatovenereologia/Resident, Dermatovenereology, Hospital de Braga, Braga, Portugal 2Especialista de Dermatovenereologia/Specialist of Dermatovenereology, Hospital de Braga, Braga, Portugal RESUMO – As dermatoses degenerativas induzidas por D-penicilamina incluem, entre outras, a elastose perfurante serpiginosa e o pseudo-pseudoxantoma elástico. A elastose perfurante serpiginosa é uma doença perfurante rara caracterizada pela elimi- nação transepidérmica de fibras elásticas anormais. Esta condição pode ser idiopática, reativa ou induzida por D-penicilamina, habitualmente utilizada para o tratamento da doença de Wilson, cistinúria, artrite reumatóide ou esclerose sistémica. Manifesta- ções cutâneas semelhantes a pseudoxantoma elástico mas sem história familiar e mutações do gene ABCC6 foram identificadas como sendo uma dermatose induzida por D-penicilamina e designada de pseudo-pseudoxantoma elástico. Descreve-se o caso de uma mulher de 17 anos tratada por vários anos com D-penicilamina para doença de Wilson, com pápulas assintomáticas, algumas cor de pele e hiperqueratósicas e outras macias e amareladas, na região cervical e face. A histopatolo- gia mostrou a eliminação transepidérmica de fibras elásticas espessadas, em forma de dentes de serra. Estes achados sugeriram uma dermopatia induzida por D-penicilamina e os autores consideraram o diagnóstico de elastose perfurante serpiginosa e pseudo-pseudoxantoma elástico no mesmo paciente. O fármaco foi alterado para acetato de zinco sem lesões novas, mas com manutenção das lesões existentes no seguimento a 1 ano. -

Analysis of Nine Cases of Oral Foreign Body Granuloma Related to Biomaterials
J Biosci (2019) 44:78 Ó Indian Academy of Sciences DOI: 10.1007/s12038-019-9898-y (0123456789().,-volV)(0123456789().,-volV) Analysis of nine cases of oral foreign body granuloma related to biomaterials 1 1 1 LARISSA SANTOS AMARAL ROLIM ,CAIO CE´ SAR DA SILVA BARROS ,JULIANA CAMPOS PINHEIRO , 2 2 PATRI´CIA TEIXEIRA DE OLIVEIRA ,LE´ LIA BATISTA DE SOUZA and 3 PEDRO PAULO DE ANDRADE SANTOS * 1Oral Pathology Post-Graduation Program Student, Federal University of Rio Grande do Norte, Natal, RN, Brazil 2Oral Pathology Post-Graduation Program, Dentistry Department, Federal University of Rio Grande do Norte, Natal, RN, Brazil 3Oral Pathology Post-Graduation Program, Morphology Department, Federal University of Rio Grande do Norte, Natal, RN, Brazil *Corresponding author (Email, [email protected]) MS received 16 September 2018; accepted 10 April 2019; published online 2 August 2019 Foreign bodies can penetrate the interior of soft and, sometimes, hard, tissues in various ways, including through open wounds, lacerations and traumatic accidents. However over the years, evidence of links between the use of dental materials and lately, significant involvement of aesthetic filler materials as foreign bodies in the oral and perioral region have been reported. Foreign body granulomas (FBGs) may develop from this exogenous material, histopathologically characterized by the presence of chronic inflammation and a high amount of macrophages. This study presents nine FBG cases affecting the oral and perioral regions, and carries out a literature review on the main clinical, histopathological and material characteristics used in dental and dermatological procedures related to the appearance of this type of granuloma. Keywords.