Certified Reference Standards for the Forensic, Clinical & Pharmaceutical Industries
Total Page:16
File Type:pdf, Size:1020Kb
Load more
Recommended publications
-

WELLBUTRIN SR Safely and Effectively
HIGHLIGHTS OF PRESCRIBING INFORMATION psychosis, hallucinations, paranoia, delusions, homicidal ideation, These highlights do not include all the information needed to use aggression, hostility, agitation, anxiety, and panic, as well as suicidal WELLBUTRIN SR safely and effectively. See full prescribing ideation, suicide attempt, and completed suicide. Observe patients information for WELLBUTRIN SR. attempting to quit smoking with bupropion for the occurrence of such symptoms and instruct them to discontinue bupropion and contact a WELLBUTRIN SR (bupropion hydrochloride) sustained-release tablets, healthcare provider if they experience such adverse events. (5.2) for oral use • Initial U.S. Approval: 1985 Seizure risk: The risk is dose-related. Can minimize risk by gradually increasing the dose and limiting daily dose to 400 mg. Discontinue if WARNING: SUICIDAL THOUGHTS AND BEHAVIORS seizure occurs. (4, 5.3, 7.3) See full prescribing information for complete boxed warning. • Hypertension: WELLBUTRIN SR can increase blood pressure. Monitor blood pressure before initiating treatment and periodically during • Increased risk of suicidal thinking and behavior in children, treatment. (5.4) adolescents and young adults taking antidepressants. (5.1) • Activation of mania/hypomania: Screen patients for bipolar disorder and • Monitor for worsening and emergence of suicidal thoughts and monitor for these symptoms. (5.5) behaviors. (5.1) • Psychosis and other neuropsychiatric reactions: Instruct patients to contact a healthcare professional if such reactions occur. (5.6) --------------------------- INDICATIONS AND USAGE ---------------------------- • Angle-closure glaucoma: Angle-closure glaucoma has occurred in WELLBUTRIN SR is an aminoketone antidepressant, indicated for the patients with untreated anatomically narrow angles treated with treatment of major depressive disorder (MDD). (1) antidepressants. -

Concomitant Drugs Associated with Increased Mortality for MDMA Users Reported in a Drug Safety Surveillance Database Isaac V
www.nature.com/scientificreports OPEN Concomitant drugs associated with increased mortality for MDMA users reported in a drug safety surveillance database Isaac V. Cohen1, Tigran Makunts2,3, Ruben Abagyan2* & Kelan Thomas4 3,4-Methylenedioxymethamphetamine (MDMA) is currently being evaluated by the Food and Drug Administration (FDA) for the treatment of post-traumatic stress disorder (PTSD). If MDMA is FDA-approved it will be important to understand what medications may pose a risk of drug– drug interactions. The goal of this study was to evaluate the risks due to MDMA ingestion alone or in combination with other common medications and drugs of abuse using the FDA drug safety surveillance data. To date, nearly one thousand reports of MDMA use have been reported to the FDA. The majority of these reports include covariates such as co-ingested substances and demographic parameters. Univariate and multivariate logistic regression was employed to uncover the contributing factors to the reported risk of death among MDMA users. Several drug classes (MDMA metabolites or analogs, anesthetics, muscle relaxants, amphetamines and stimulants, benzodiazepines, ethanol, opioids), four antidepressants (bupropion, sertraline, venlafaxine and citalopram) and olanzapine demonstrated increased odds ratios for the reported risk of death. Future drug–drug interaction clinical trials should evaluate if any of the other drug–drug interactions described in our results actually pose a risk of morbidity or mortality in controlled medical settings. 3,4-Methylenedioxymethamphetamine (MDMA) is currently being evaluated by the Food and Drug Adminis- tration (FDA) for the treatment of posttraumatic stress disorder (PTSD). During the past two decades, “ecstasy” was illegally distributed and is purported to contain MDMA, but because the market is unregulated this “ecstasy” may actually contain adulterants or no MDMA at all1. -

DART-MS/MS Screening for the Determination of 1,3- Dimethylamylamine and Undeclared Stimulants in Seized Dietary Supplements from Brazil
Forensic Chemistry 8 (2018) 134–145 Contents lists available at ScienceDirect Forensic Chemistry journal homepage: www.elsevier.com/locate/forc DART-MS/MS screening for the determination of 1,3- dimethylamylamine and undeclared stimulants in seized dietary supplements from Brazil Maíra Kerpel dos Santos a, Emily Gleco b, J. Tyler Davidson b, Glen P. Jackson b, Renata Pereira Limberger a, ⇑ Luis E. Arroyo b, a Graduate Program of Pharmaceutical Sciences, Faculty of Pharmacy, Federal University of Rio Grande do Sul, Brazil b Department of Forensic & Investigative Science, West Virginia University, USA article info abstract Article history: 1,3-dimethylamylamine (DMAA) is an alkylamine with stimulating properties that has been used pre- Received 15 December 2017 dominantly as an additive in dietary supplements. DMAA is mostly consumed by professional athletes, Received in revised form 14 March 2018 and several doping cases reported since 2008 led to its prohibition by the World Anti-Doping Agency Accepted 18 March 2018 (WADA) in 2010. Adverse effects have indicated DMAA toxicity, and there is few data regarding its safety, Available online 22 March 2018 so it was banned by regulatory agencies from Brazil and the United States. Ambient ionization methods such as Direct Analysis in Real Time Tandem Mass Spectrometry (DART-MS/MS) are an alternative for Keywords: dietary supplements analysis, because they enable the analysis of samples at atmospheric pressure in 1,3-dimethylamylamine a very short time and with only minimal sample preparation. Therefore, the aim of this work was to DART-MS/MS Dietary supplements develop a methodology by DART-MS/MS to detect the presence of DMAA, ephedrine, synephrine, caffeine, Stimulants sibutramine, and methylphenidate in 108 dietary supplements seized by the Brazilian Federal Police Adulterants (BFP). -

(19) United States (12) Patent Application Publication (10) Pub
US 20130289061A1 (19) United States (12) Patent Application Publication (10) Pub. No.: US 2013/0289061 A1 Bhide et al. (43) Pub. Date: Oct. 31, 2013 (54) METHODS AND COMPOSITIONS TO Publication Classi?cation PREVENT ADDICTION (51) Int. Cl. (71) Applicant: The General Hospital Corporation, A61K 31/485 (2006-01) Boston’ MA (Us) A61K 31/4458 (2006.01) (52) U.S. Cl. (72) Inventors: Pradeep G. Bhide; Peabody, MA (US); CPC """"" " A61K31/485 (201301); ‘4161223011? Jmm‘“ Zhu’ Ansm’ MA. (Us); USPC ......... .. 514/282; 514/317; 514/654; 514/618; Thomas J. Spencer; Carhsle; MA (US); 514/279 Joseph Biederman; Brookline; MA (Us) (57) ABSTRACT Disclosed herein is a method of reducing or preventing the development of aversion to a CNS stimulant in a subject (21) App1_ NO_; 13/924,815 comprising; administering a therapeutic amount of the neu rological stimulant and administering an antagonist of the kappa opioid receptor; to thereby reduce or prevent the devel - . opment of aversion to the CNS stimulant in the subject. Also (22) Flled' Jun‘ 24’ 2013 disclosed is a method of reducing or preventing the develop ment of addiction to a CNS stimulant in a subj ect; comprising; _ _ administering the CNS stimulant and administering a mu Related U‘s‘ Apphcatlon Data opioid receptor antagonist to thereby reduce or prevent the (63) Continuation of application NO 13/389,959, ?led on development of addiction to the CNS stimulant in the subject. Apt 27’ 2012’ ?led as application NO_ PCT/US2010/ Also disclosed are pharmaceutical compositions comprising 045486 on Aug' 13 2010' a central nervous system stimulant and an opioid receptor ’ antagonist. -

Multi-Class Determination of 64 Illicit Compounds in Dietary Supplements Using Liquid Chromatography–Tandem Mass Spectrometry
molecules Article Multi-Class Determination of 64 Illicit Compounds in Dietary Supplements Using Liquid Chromatography–Tandem Mass Spectrometry Dasom Shin, Hui-Seung Kang *, Hyungsoo Kim and Guiim Moon New Hazardous Substances Division, Department of Food Safety Evaluation, National Institute of Food and Drug Safety Evaluation, Ministry of Food and Drug Safety, Osong, Cheongju 28159, Korea; [email protected] (D.S.); [email protected] (H.K.); [email protected] (G.M.) * Correspondence: [email protected] Received: 11 August 2020; Accepted: 17 September 2020; Published: 24 September 2020 Abstract: In this work, liquid chromatography–tandem mass spectrometry (LC-MS/MS) method was developed and validated for screening and confirmation of 64 illicit compounds in dietary supplements. The target compounds were illegally used pharmaceutical drugs, prohibited compounds, and not authorized ingredients for different therapeutics (sexual enhancement, weight loss, muscular strengthening, and relaxing products). The validation procedure was performed to evaluate selectivity, linearity, limit of detection (LOD), limit of quantification (LOQ), accuracy, and precision according to the Association of Official Analytical Chemists guidelines. The linearity was >0.98 in the range of 1 1 0.5–200 µg L− . The LOQs were in the range 1–10 µg kg− for all target compounds. The accuracy (expressed as recovery) was 78.5–114%. The precision (expressed as the relative standard deviation) was below 9.15%. The developed method was applied for the determination of illicit compounds in dietary supplements collected from websites. As a result, the total detection rate was 13.5% (27 samples detected in 200 samples). The concentrations of detected samples ranged from 0.51 1 to 226 mg g− . -

Stimulant Medications and Supplements: Clinical Implications for the Sports Medicine Provider Collaborative Solutions for Safety in Sport
Stimulant Medications and Supplements: Clinical Implications for the Sports Medicine Provider Collaborative Solutions for Safety in Sport Francis G. O’Connor, MD, MPH, COL, MC, USA Professor and Chair, Military and Emergency Medicine Uniformed Services University of the Health Sciences DISCLOSURE . I have no relevant financial disclosures in reference to this lecture. That being said, I am a physician in the US Army, and work for the DoD. My opinions and assertions contained herein are private views and are not to be construed as official or as reflecting the views of the U.S. Army Medical Department , Uniformed Services University or the Department of Defense at large. Case Presentation 1 . 25 y/o soldier presents to the sports medicine clinic for heat tolerance testing and a return to duty assessment; . He sustained an exertional heat stroke (EHS) during Special Forces accession. Soldier was acclimatized with no history of EHS; he had been using a pre- workout stimulant. Case Presentation 2 . 25 y/o soldier presents to the medical aid station complaining of palpitations, agitation and insomnia. He has sinus tachycardia on the monitor and reports regular use of Red Bull and caffeine gum. Unit is requesting guidance on strategies for sleep. Case Presentation 3 . A warfighter contacts the Human Performance Resource Center looking for help. Recently using a new pre- workout supplement to enhance training. Unfortunately the soldier “popped positive” on a recent urine drug screen. Case Presentation 4 . Alison is a 19 y/o transfer female basketball player. She states she has a personal history of ADHD and would like to renew her prescription for Ritalin. -

MEDICATION GUIDE WELLBUTRIN® (WELL Byu-Trin) (Bupropion Hydrochloride) Tablets
NDA 018644/S-041 NDA 020358/S-048 Page 6 MEDICATION GUIDE WELLBUTRIN® (WELL byu-trin) (bupropion hydrochloride) Tablets Read this Medication Guide carefully before you start using WELLBUTRIN and each time you get a refill. There may be new information. This information does not take the place of talking with your doctor about your medical condition or your treatment. If you have any questions about WELLBUTRIN, ask your doctor or pharmacist. IMPORTANT: Be sure to read the three sections of this Medication Guide. The first section is about the risk of suicidal thoughts and actions with antidepressant medicines; the second section is about the risk of changes in thinking and behavior, depression and suicidal thoughts or actions with medicines used to quit smoking; and the third section is entitled “What Other Important Information Should I Know About WELLBUTRIN?” Antidepressant Medicines, Depression and Other Serious Mental Illnesses, and Suicidal Thoughts or Actions This section of the Medication Guide is only about the risk of suicidal thoughts and actions with antidepressant medicines. Talk to your, or your family member’s, healthcare provider about: • all risks and benefits of treatment with antidepressant medicines • all treatment choices for depression or other serious mental illness What is the most important information I should know about antidepressant medicines, depression and other serious mental illnesses, and suicidal thoughts or actions? 1. Antidepressant medicines may increase suicidal thoughts or actions in some children, teenagers, and young adults within the first few months of treatment. 2. Depression and other serious mental illnesses are the most important causes of suicidal thoughts and actions. -

Chiral Separation for Enantiomeric Determination in the Pharmaceutical Industry
Chapter CHIRAL SEPARATION FOR ENANTIOMERIC DETERMINATION IN THE PHARMACEUTICAL INDUSTRY Nelu Grinberg, Su Pan Contents 6.1. INTRODUCTION ...................................................................................................................................... 235 6.2. ENANTIOMERS, DIASTEREOMERS, RACEMATES ................................................................... 236 6.3. REQUIREMENTS FOR CHIRAL SEPARATION ............................................................................ 237 6.4. THE TYPES OF MOLECULAR INTERACTIONS ........................................................................... 237 6.4.1. Chiral separation through hydrogen bonding ............................................................. 237 6.4.2. Chiral separation through inclusion compounds ....................................................... 243 6.4.2.1. Cyclodextrins ............................................................................................................ 243 6.4.2.2. Crown ethers ............................................................................................................. 245 6.4.3. Charge transfer .......................................................................................................................... 259 6.4.4. Chiral separation through a combination of charge transfer, hydrogen bonding and electrostatic interactions ........................................................................... 260 233 Chapter 6 6.4.5. Ligand exchange ...................................................................................................................... -

Antidepressant & Psychedelic Drug Interaction Chart
Copyright Psychedelic School 8/2020 Antidepressant & Psychedelic Drug Interaction Chart This chart is not intended to be used to make medical decisions and is for informational purposes only. It was constructed using data whenever possible, although extrapolation from known information was also used to inform risk. Any decision to start, stop, or taper medication and/or use psychedelic drugs should be made in conjunction with your healthcare provider(s). It is recommended to not perform any illicit activity. This chart the intellectual property of psychedelic school and is for personal use only. Please do not copy or distribute this chart. Antidepressant Phenethylamines Tryptamines MAOI-containing Ketamine Ibogaine -MDMA, mescaline -Psilocybin, LSD -Ayahuasca, Syrian Rue SSRIs Taper & discontinue at least 2 Consider taper & Taper & discontinue at least 2 Has been studied and Taper & discontinue at · Paroxetine (Paxil) weeks prior (all except discontinuation at least 2 weeks weeks prior (all except found effective both with least 2 weeks prior (all · Sertraline (Zoloft) fluoxetine) or 6 weeks prior prior (all except fluoxetine) or 6 fluoxetine) or 6 weeks prior and without concurrent except fluoxetine) or 6 · Citalopram (Celexa) (fluoxetine only) due to loss of weeks prior (fluoxetine only) (fluoxetine only) due to use of antidepressants weeks prior (fluoxetine · Escitalopram (Lexapro) psychedelic effect due to potential loss of potential risk of serotonin only) due to risk of · Fluxoetine (Prozac) psychedelic effect syndrome additive QTc interval · Fluvoxamine (Luvox) MDMA is unable to cause Recommended prolongation, release of serotonin when the Chronic antidepressant use may Life threatening toxicities can to be used in conjunction arrhythmias, or SPARI serotonin reuptake pump is result in down-regulation of occur with these with oral antidepressants cardiotoxicity · Vibryyd (Vilazodone) blocked. -
Prohibited Substances List
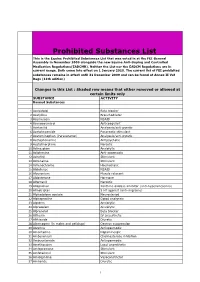
Prohibited Substances List This is the Equine Prohibited Substances List that was voted in at the FEI General Assembly in November 2009 alongside the new Equine Anti-Doping and Controlled Medication Regulations(EADCMR). Neither the List nor the EADCM Regulations are in current usage. Both come into effect on 1 January 2010. The current list of FEI prohibited substances remains in effect until 31 December 2009 and can be found at Annex II Vet Regs (11th edition) Changes in this List : Shaded row means that either removed or allowed at certain limits only SUBSTANCE ACTIVITY Banned Substances 1 Acebutolol Beta blocker 2 Acefylline Bronchodilator 3 Acemetacin NSAID 4 Acenocoumarol Anticoagulant 5 Acetanilid Analgesic/anti-pyretic 6 Acetohexamide Pancreatic stimulant 7 Acetominophen (Paracetamol) Analgesic/anti-pyretic 8 Acetophenazine Antipsychotic 9 Acetylmorphine Narcotic 10 Adinazolam Anxiolytic 11 Adiphenine Anti-spasmodic 12 Adrafinil Stimulant 13 Adrenaline Stimulant 14 Adrenochrome Haemostatic 15 Alclofenac NSAID 16 Alcuronium Muscle relaxant 17 Aldosterone Hormone 18 Alfentanil Narcotic 19 Allopurinol Xanthine oxidase inhibitor (anti-hyperuricaemia) 20 Almotriptan 5 HT agonist (anti-migraine) 21 Alphadolone acetate Neurosteriod 22 Alphaprodine Opiod analgesic 23 Alpidem Anxiolytic 24 Alprazolam Anxiolytic 25 Alprenolol Beta blocker 26 Althesin IV anaesthetic 27 Althiazide Diuretic 28 Altrenogest (in males and gelidngs) Oestrus suppression 29 Alverine Antispasmodic 30 Amantadine Dopaminergic 31 Ambenonium Cholinesterase inhibition 32 Ambucetamide Antispasmodic 33 Amethocaine Local anaesthetic 34 Amfepramone Stimulant 35 Amfetaminil Stimulant 36 Amidephrine Vasoconstrictor 37 Amiloride Diuretic 1 Prohibited Substances List This is the Equine Prohibited Substances List that was voted in at the FEI General Assembly in November 2009 alongside the new Equine Anti-Doping and Controlled Medication Regulations(EADCMR). -

Methedrine, Neo-Synephrine, Paredrine, and Pholedrine
Br Heart J: first published as 10.1136/hrt.6.4.214 on 1 October 1944. Downloaded from CLINICAL EVALUATION OF THE PRESSOR ACTIVITY OF METHEDRINE, NEO-SYNEPHRINE, PAREDRINE, AND PHOLEDRINE BY FREDERICK PRESCOTT From the Wellcome Research Institution, London Received October 10, 1944 Recently a number of pressor drugs of the adrenaline type have come into clinical use for the treatment of low blood pressure following surgical procedures, spinal anxsthesia, circu- latory collapse, and surgical and traumatic shock. For therapeutic purposes the ideal pressor drug should be effective by the intramuscular or intravenous route; it should act rapidly; it should produce a sustained elevation of blood pressure, so that frequent injections of the drug are not necessary; and it should have no undesirable effects on the cardiovascular system and no untoward side effects. Adrenaline and ephedrine were the first drugs to be used clinically to raise the blood pressure in cases of operative shock. Their limitations, however, are nowv well known. Adrenaline may do more harm than good beca4se in thera- peutic doses intrayenously it causes a considerable rise of blood pressure, e.g. 200 mm. to 300 mm. of mercury, with a precipitous fall after a few minutes to a level lower than before. Similarly ephedrine, which for dependable results must be given intravenously, produces a http://heart.bmj.com/ sharp rise of blood pressure that lasts only for ten to twenty minutes. Other pressor drugs have been introduced with a more sustained action. In most of the studies reported on these, however, no definite criteria seem to have been employed in their evaluation, nor have the conditions of administration been standardized. -

Phd Thesis Project: Pharmacological and Toxicological Investigations of New Psychoactive Substances, Supervised by Prof
PHARMACOLOGICAL AND TOXICOLOGICAL INVESTIGATIONS OF NEW PSYCHOACTIVE SUBSTANCES Inauguraldissertation zur Erlangung der Würde eines Doktors der Philosophie vorgelegt der Philosophisch-Naturwissenschaftlichen Fakultät der Universität Basel von Dino Lüthi aus Rüderswil, Bern Basel, 2018 Originaldokument gespeichert auf dem Dokumentenserver der Universität Basel edoc.unibas.ch Dieses Werk ist lizenziert unter einer Creative Commons Namensnennung-Nicht kommerziell 4.0 International Lizenz (https://creativecommons.org/licenses/by-nc-sa/4.0/deed.de). Genehmigt von der Philosophisch-Naturwissenschaftlichen Fakultät auf Antrag von Prof. Stephan Krähenbühl, Prof. Matthias E. Liechti und Prof. Anne Eckert. Basel, den 26.06.2018 Prof. Martin Spiess Dekan der Philosophisch- Naturwissenschaftlichen Fakultät PHARMACOLOGICAL AND TOXICOLOGICAL INVESTIGATIONS OF NEW PSYCHOACTIVE SUBSTANCES “An adult must make his own decision as to whether or not he should expose himself to a specific drug, be it available by prescription or proscribed by law, by measuring the potential good and bad with his own personal yardstick.” ― Alexander Shulgin, Pihkal: A Chemical Love Story. PREFACE This thesis is split into a pharmacology part and a toxicology part. The pharmacology part consists of investigations on the monoamine transporter and receptor interactions of traditional and newly emerged drugs, mainly stimulants and psychedelics; the toxicology part consists of investigations on mechanisms of hepatocellular toxicity of synthetic cathinones. All research described in this thesis has been published in peer-reviewed journals, and was performed between October 2014 and June 2018 in the Division of Clinical Pharmacology and Toxicology at the Department of Biomedicine of the University Hospital Basel and University of Basel, and partly at the pRED Roche Innovation Center Basel at F.