
MASSAGE CLIENT INTAKE FORM
Client Name: ______Email Address: ______Home Phone: ______Cell Phone: ______Emergency Contact: ______Relationship: ______Phone: ______Address: ______City: ______State: _____ Zip: ______Height ______Weight ______DOB: ______Occupation: ______MAJOR COMPLAINT ______MINOR COMPLAINT ______Have you ever had a professional massage before? Yes No If yes, what type: Swedish / Deep Tissue / Neuromuscular / Shiatsu / Reflexology Do you have a style or pressure preference? Specify: light pressure medium pressure deep pressure How did you find out about Massage Therapy here at Magnolia PT? ______
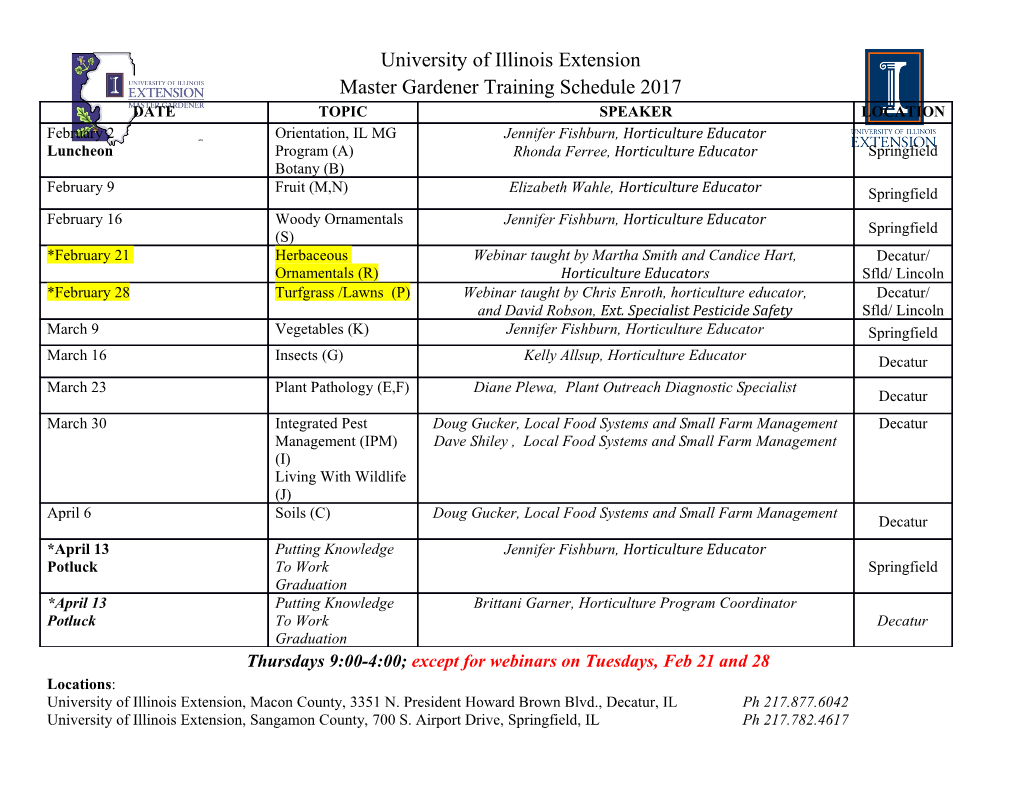
BLOOD PRESSURE High / Low Medication: ______Diabetes: Yes No Medication: ______Heart Condition: ______Back Pain: Upper Mid Lower Pinched Nerves: Yes No TMJ: Yes No Headaches / Migraines: Yes No Tumors / Cysts: Yes No Allergies: Yes No Sinus: Yes No Skin Disorders / Sensitive Skin: Yes No Do you wear contacts: Yes No
Please list any other medical conditions, surgeries, or accidents:
______
______Are you presently under the care of a physician? Yes No (if yes, please give name and condition being seen for)
______
Draping: LA law requires keeping the unclothed body properly draped at all times. This is necessary for your warmth and sense of ease as well as a mark of professionalism.
Release and Consent: I understand that the massage I will be receiving here is for the purpose of stress reduction and relief from muscular tension or spasm. I understand that massage is not a substitute for medical treatment. I know and agree that Magnolia Physical Therapy, LLC is not responsible for loss or damage to personal items. I hereby freely give permission to be managed. I agree and understand that I am responsible to immediately inform the massage therapist of any pain or unusual sensitivity during the massage or prior to receiving massage in the future. If you have been diagnosed with cancer or any other severe medical conditions we require a written Physician’s release. I understand that payment is due at the time services are rendered and that massage therapy here at Magnolia Physical Therapy is an out of pocket expense which is not covered by insurance.
Signature ______Date ______
Massage Therapist Signature ______Date ______
Details
-
File Typepdf
-
Upload Time-
-
Content LanguagesEnglish
-
Upload UserAnonymous/Not logged-in
-
File Pages2 Page
-
File Size-